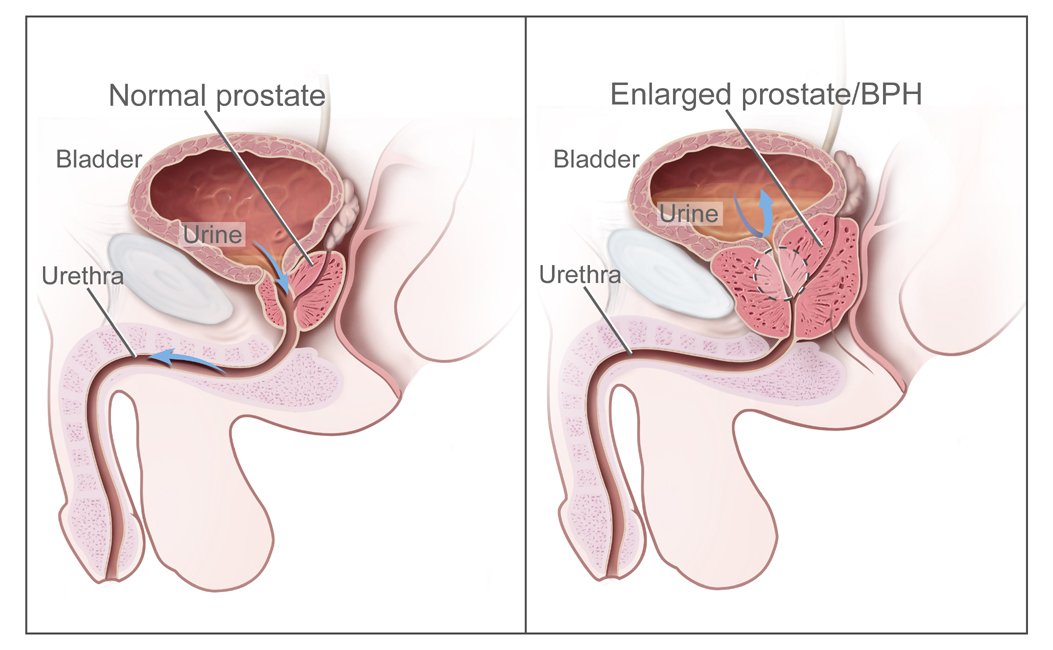
相邻结构承担不同功能
盆底是由肌肉、结缔组织和神经等构成的区域,支撑盆腔器官,并参与排尿、排便和性功能相关的协调。前列腺位于膀胱下方,包绕尿道起始的一部分;膀胱储存尿液,尿道则将尿液排出体外。结构彼此相邻并不表示功能相同,也不表示一个部位出现症状就一定来自另一个部位。
前列腺会随年龄发生变化,但前列腺增生、炎症、感染和癌症是不同概念。良性前列腺增生可能压迫尿道并与尿流变弱、排尿启动困难、频繁或夜间排尿等症状相关;然而类似症状也可能来自膀胱、尿道、药物、神经系统或其他健康状况。症状严重程度也不总能与腺体大小对应,因此不能通过症状自行确认诊断。
观察症状的时间与组合
理解泌尿变化时,发生多久、如何变化、一天中何时明显、是否伴随疼痛或发热,以及饮水和用药背景都可能有帮助。尿频、尿急、夜尿、尿流改变、排尿疼痛和血尿背后的原因并不相同。突然无法排尿、明显血尿、发热伴寒战或严重疼痛等情况可能需要尽快医疗评估;具体紧急程度应由所在地医疗服务判断。
长期症状会影响睡眠和生活质量,值得讨论。临床评估可能包括病史、体格检查、尿液检测或其他检查,项目会因年龄、风险和症状而不同。某些筛查或检测也有局限,需要在利弊和个人偏好基础上沟通。网络描述无法替代检查;不要因为担心前列腺问题而自行停用利尿剂、感冒药或其他处方药。
盆底训练并非人人相同
盆底肌肉参与支撑和控制,但“加强盆底”并不是所有盆底问题的统一答案。部分人可能存在协调不足或肌肉过度紧张,反复收缩反而可能增加不适。盆底训练的适用性取决于症状、肌肉功能及专业评估;如果动作引起疼痛、排尿更困难或其他不适,应停止自行练习并询问医疗人员或合格的盆底康复专业人员。
研究对盆底训练的关注常集中在特定人群和特定结局,例如术后康复或尿失禁,不能把这些结果概括成适用于所有男性的性功能方案。练习方法、监督方式和研究质量存在差异。未经评估的网络课程或器械不一定适合个人情况,也可能造成延误。
把泌尿健康放回整体背景
前列腺或尿路症状不是男性身份或性能力的判断标准。泌尿、性功能、睡眠、慢性病和心理压力可能互相影响,但单一症状无法说明全部原因。持续困扰、症状变化或出现警示表现时,专业评估可以帮助区分可能路径。记录症状开始时间、变化趋势和正在使用的药物,能提供背景信息,但不能替代诊断。
本文仅介绍一般解剖和健康信息。若出现急剧恶化、无法排尿、发热寒战、明显出血或剧烈疼痛,请联系当地医疗服务寻求及时评估。药物、训练和检查选择都需结合个人情况讨论,不应仅依据网络内容作出决定。
把一次体验放回更大的背景
健康文章可以帮助读者认识术语和可能的影响因素,却不能把复杂体验压缩成一个结论。勃起、射精、性欲和排尿都可能随着睡眠、压力、关系、疾病、药物以及生活阶段而变化。观察变化开始的时间、发生频率、是否在不同情境出现,以及它是否影响生活,往往比寻找一个“标准表现”更有信息量。不同人的基线本来就不一样,偶尔波动也不等同于疾病。
研究结果还需要看它是怎样得到的。问卷、门诊记录、实验室指标和随机试验回答的问题不同;相关性也不自动等于因果关系。网络文章如果只引用单个数字、单个补充剂或一项检测,就可能把不确定性隐藏起来。更稳妥的阅读方式是同时看研究对象、时间范围、比较方式和作者承认的限制,并把结论限定在证据真正覆盖的范围内。
如果变化持续、反复或让你困扰,可以把时间线、伴随症状和正在使用的药物记录下来,再通过当地正规医疗渠道讨论。突然出现剧烈疼痛、明显呼吸困难、昏厥、持续胸痛或其他急症信号时,应优先获得紧急帮助。本文只提供一般教育,不替代对个人情况的评估,也不建议根据网络内容自行开始、停止或调整药物。
盆底、前列腺和尿路问题可能共享一些症状,也可能完全无关。排尿频率、尿流改变、疼痛和性功能变化的时间线比笼统标签更值得记录。
把信息转成可核对的问题
阅读后可以写下三个问题:这条结论研究了谁、它能解释我正在观察的哪一部分、还有哪些替代解释没有被排除。带着具体问题和完整时间线寻求专业帮助,通常比在多个网页之间反复比较单一数字更有效。
Nearby structures have different roles
The pelvic floor is an area of muscles, connective tissue and nerves that supports pelvic organs and contributes to coordination involved in urination, bowel function and sexual activity. The prostate sits below the bladder and surrounds part of the urethra near its beginning. The bladder stores urine, while the urethra carries it out of the body. These structures are close, but they do not have identical functions. A symptom in one area does not automatically identify another structure as its source.
The prostate changes with age, but enlargement, inflammation, infection and cancer are different concepts. Benign prostatic enlargement can press on the urethra and may be associated with a weak stream, difficulty starting, frequent urination or waking at night. Similar symptoms can also arise from the bladder, urethra, medicines, neurological conditions or other health issues. Symptom severity does not always match prostate size, so symptoms alone cannot confirm a diagnosis.
Consider timing and combinations of symptoms
The duration and pattern of a urinary change, when it is most noticeable, associated pain or fever, hydration and medicines can all provide context. Frequency, urgency, nighttime urination, stream changes, painful urination and blood in urine do not share one cause. Inability to urinate suddenly, visible blood, fever with chills or severe pain may call for prompt medical assessment. Local services can advise on the appropriate urgency.
Persistent symptoms can affect sleep and quality of life and are reasonable to discuss. Assessment may include history, examination, urine tests or other investigations depending on age, risk and symptoms. Some screening tests have limitations and require discussion of benefits, harms and personal preferences. An online description cannot replace an examination. Do not stop a diuretic, cold medicine or other prescription on your own because of concern about the prostate.
Pelvic-floor exercises are not the same for everyone
Pelvic-floor muscles contribute to support and control, but “strengthen the pelvic floor” is not a universal answer to every pelvic-floor concern. Some people may have difficulty coordinating or relaxing these muscles; repeated contractions could increase discomfort. Whether exercises are appropriate depends on symptoms, muscle function and assessment. If an exercise causes pain, makes urination harder or creates another problem, stop self-directed practice and ask a health professional or qualified pelvic rehabilitation clinician.
Research on pelvic-floor training often focuses on particular groups and outcomes, such as rehabilitation after surgery or urinary leakage. Those findings should not be generalized into a sexual-function program for every man. Methods, supervision and study quality vary. An online course or device used without assessment may not fit an individual’s needs and could delay appropriate care.
Place urinary health in the broader context
Prostate or urinary symptoms do not define masculinity or sexual ability. Urinary function, sexual health, sleep, chronic illness and stress may interact, but one symptom cannot explain the whole picture. When a concern persists, changes or includes warning signs, professional assessment can help distinguish possible pathways. A note of when symptoms began, how they have changed and which medicines are used can provide context, but it is not a diagnosis.
This article offers general anatomical and health information only. Rapid deterioration, inability to urinate, fever with chills, visible bleeding or severe pain warrants timely contact with local medical services. Decisions about medicines, exercises and tests need personal context and should not rely on online content alone.
Putting one experience in a wider context
Health education can explain terms and possible influences, but it cannot compress a complex experience into one conclusion. Erections, ejaculation, desire and urinary symptoms may vary with sleep, stress, relationships, illness, medicines and life stage. The timing, frequency, context and effect on daily life often provide more useful information than searching for a single “normal performance”. People also begin from different baselines, and an occasional change is not the same as a disease.
Evidence needs to be read through its design. A questionnaire, a clinic record, a laboratory measure and a randomised trial answer different questions; an association is not automatically a cause. If an online article cites one number, one supplement or one test, it may be hiding uncertainty. A more careful reading asks who was studied, for how long, what was compared and which limitations the authors acknowledge. Conclusions should stay within the population and outcome that the evidence actually covered.
If a change persists, repeats or causes distress, a timeline of symptoms, related changes and current medicines can support a conversation through appropriate local care. Sudden severe pain, marked breathlessness, fainting, persistent chest pain or another emergency sign deserves urgent help rather than online confirmation. This article is general education, not an assessment of an individual, and it does not advise starting, stopping or changing a medicine from web information alone.
Pelvic, prostate and urinary concerns may share symptoms or may be unrelated. The timeline of frequency, flow change, pain and sexual symptoms is more useful than a broad label alone.
Turning information into checkable questions
After reading, write down three questions: who was studied, which part of the experience could the finding explain, and which alternative explanations remain open. Bringing those questions and a complete timeline to an appropriate health professional is usually more useful than comparing one number across many web pages.